 Skip to content

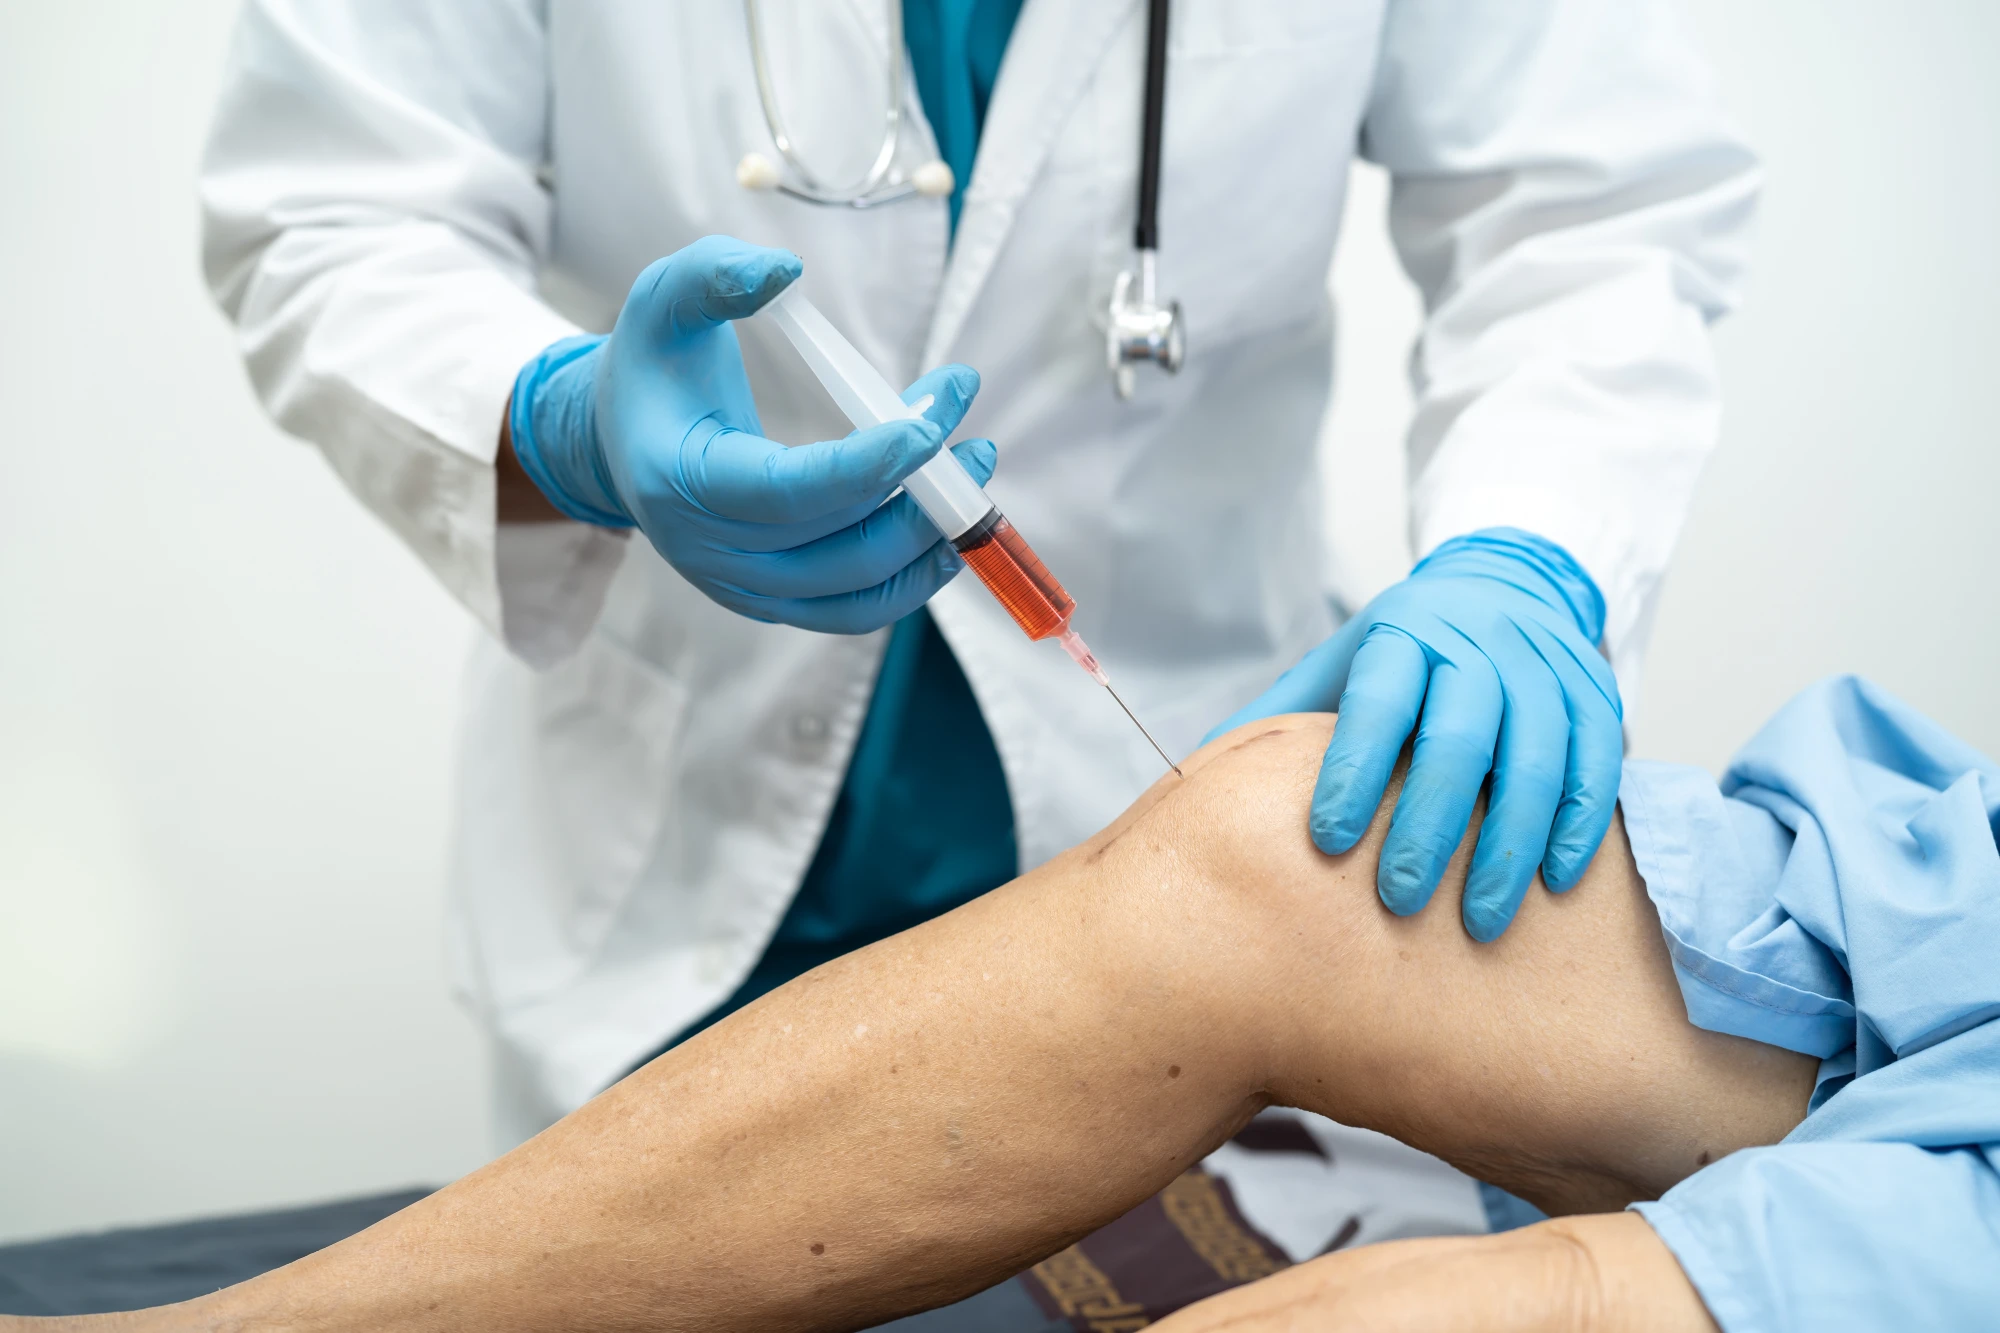




Knee pain? Maybe.
Chronic shoulder pain? Possibly.
A tendon that has bothered you for months? Worth evaluating.
A brand-new swollen joint after an injury? Not so fast.
One of the biggest misconceptions about regenerative joint treatment is that anyone with joint pain is automatically a candidate.
They are not.
The diagnosis matters. The severity matters. The age of the injury matters. Stability matters. Imaging matters. And sometimes the safest and most effective next step is physical therapy, orthopedic surgery, additional imaging, or treatment of another underlying condition.
At The Re/ Clinic in Sandy, Utah, regenerative treatment begins with determining what is actually causing the pain and whether a biologic procedure is reasonable to consider.
Here is how that candidacy discussion works.
Table of Contents
Quick Answer: Who May Be a Candidate for Regenerative Joint Treatment?
Patients who may be reasonable candidates to evaluate for regenerative treatment often have chronic musculoskeletal symptoms such as:
- Osteoarthritis
- Persistent joint pain
- Chronic tendinopathy
- Repetitive-use injuries
- Certain partial tendon or ligament injuries
- Some meniscal or cartilage injuries
- Persistent shoulder, elbow, knee, hip, ankle, or foot pain
- Symptoms that have not improved enough with conservative care
The word evaluate is important.
None of those diagnoses automatically means a regenerative procedure is the right treatment.
The current evidence for orthobiologics varies considerably by condition and by product. Recent reviews describe promising results in some areas while emphasizing heterogeneous protocols, inconsistent evidence, and a continued need for higher-quality trials.
Patients who may need another evaluation or treatment first include those with:
- Active joint or systemic infection
- A new severe traumatic injury
- Suspected fracture or dislocation
- A displaced meniscal tear causing mechanical locking
- An unstable complete ligament tear
- Severe neurological symptoms associated with back pain
- Advanced structural joint damage where joint replacement may be the more appropriate option
The goal should never be to make the patient fit the procedure.
The goal is to determine which treatment best fits the patient.
Watch: Dr. John Dame’s Rapid-Fire Regenerative Treatment Candidate Check
Video Transcript
Dr. John Dame:
Knee pain? Yes.
Acutely injured joint? No. Any active inflammation, not a good plan.
Shoulder pain that won’t go away? Yes.
Chronic back pain? Yes.
Active joint infection? No. No infections. No good.
Elbow pain from repetitive use? Yes.
Heel pain when you walk? Yes.
Nagging tendon pain? Yes.
Torn cartilage in your knee? Yes.
Fully torn ligament? Yes, with a caveat.
Completely worn-down joints? Yes, with some benefit.
Joint pain from aging? Absolutely.
Important Context About the Video
This video is intentionally fast.
Real candidacy is not.
A few of Dr. Dame’s answers need additional context before being applied to an individual patient.
“Acutely injured joint? No.”
A new injury should generally be diagnosed before jumping directly to a regenerative injection.
An acute injury might involve:
- Fracture
- Dislocation
- Complete tendon rupture
- Ligament rupture
- Acute meniscal tear
- Significant cartilage injury
- Joint infection
Some acute injuries require timely orthopedic management.
For example, current AAOS guidance states that displaced acute meniscal tears restricting knee movement may benefit from early surgical intervention, while some repairable tears should also be considered for early surgery.
So the message is less:
“Regenerative medicine can never be used after an acute injury.”
and more:
“Do not treat an undiagnosed acute injury as though it were routine chronic joint pain.”
“Any active inflammation? Not a good plan.”
This also needs nuance.
Osteoarthritis itself can involve inflammatory signaling, so the presence of inflammation does not automatically exclude someone from consideration.
What raises more concern is a new, hot, significantly swollen, acutely inflamed joint, especially when the cause is unknown.
That situation needs evaluation first.
“Chronic back pain? Yes.”
Chronic back pain is a symptom, not one diagnosis.
Back pain can originate from discs, joints, nerves, muscles, stenosis, instability, previous surgery, or other causes.
A procedure should be based on a specific diagnosis rather than treating “back pain” as one uniform condition.
The FDA also specifically states that regenerative medicine products have not been approved for orthopedic conditions including back pain and disc disease.
“Fully torn ligament? Yes, with a caveat.”
The caveat is important.
A biologic injection should not automatically be viewed as a substitute for reconstruction when a complete tear has created mechanical instability.
For example, AAOS guidance for common midsubstance ACL tears strongly favors ACL reconstruction over repair because of lower revision rates, particularly when surgical treatment is indicated.
“Completely worn-down joints? Yes, with some benefit.”
Patients with advanced arthritis may still want to discuss nonsurgical options, but severe structural degeneration can limit what any injection can realistically accomplish.
Regenerative treatment does not replace missing joint architecture or mechanically reconstruct a severely damaged joint.
For some patients with advanced disease, joint-replacement evaluation may remain the more appropriate pathway.
1. Knee Pain: Maybe
Knee pain is one of the most common reasons patients research regenerative medicine.
But “knee pain” can describe very different conditions:
- Osteoarthritis
- Meniscus injury
- Patellar tendinopathy
- Ligament injury
- Cartilage damage
- Bursitis
- Patellofemoral pain
- Referred pain
The evidence for cell-based therapies is most developed in knee osteoarthritis, although results remain heterogeneous.
Several recent meta-analyses of randomized trials have reported improvements in pain and function after MSC treatment compared with certain control groups. At the same time, researchers continue to note major differences in cell source, preparation, dose, study design, and patient selection.
That means knee pain can be a reason to schedule an evaluation.
It does not mean every painful knee should receive the same injection.
2. A Newly Injured Joint: Diagnose It First
Imagine you twist your knee skiing yesterday.
Today it is swollen, painful, and difficult to bear weight on.
That is different from having knee arthritis for five years.
An acute injury should first be evaluated for problems that could require timely treatment.
Depending on the injury, that may involve:
- Physical examination
- X-rays
- MRI
- Orthopedic consultation
- Temporary activity restriction
- Physical therapy
- Surgical evaluation
For acute meniscal tears, AAOS currently recommends MRI as the preferred imaging modality because of its diagnostic accuracy. Certain displaced tears and repairable injuries may warrant earlier surgical management.
So in the rapid-fire video:
Acute injury = pause and diagnose.
3. Persistent Shoulder Pain: Possibly
Shoulder pain that has persisted despite rest, rehabilitation, or other conservative treatment can be reasonable to evaluate.
Possible causes include:
- Rotator cuff tendinopathy
- Partial rotator cuff tear
- Full-thickness tear
- Labral injury
- Biceps tendon problems
- Osteoarthritis
- Adhesive capsulitis
- Impingement-related symptoms
Those conditions are not interchangeable.
The AAOS updated its rotator cuff injury guideline in 2025, reflecting the fact that treatment decisions depend on factors such as tear type, severity, function, and patient characteristics.
This is why someone with:
“shoulder pain that won’t go away”
might deserve a regenerative consultation, but the evaluation still needs to determine why the shoulder hurts.
4. Chronic Back Pain: Diagnosis Matters
A patient may have had low-back pain for years and still not know the exact pain generator.
Potential sources can include:
- Degenerative disc changes
- Facet joints
- Sacroiliac joints
- Muscles
- Nerve compression
- Spinal stenosis
- Previous injury
- Multiple overlapping causes
The American College of Radiology distinguishes uncomplicated chronic back pain from back pain associated with red flags such as suspected infection, cancer, cauda equina syndrome, or progressive symptoms. Those scenarios require a different diagnostic pathway.
So chronic back pain may be worth evaluating.
But:
“My back hurts” is not enough information to determine candidacy.
5. Active Joint Infection: No
This is one of the clearest answers in the video.
An actively infected joint is not an appropriate situation for an elective regenerative injection.
Joint infection can rapidly damage cartilage and surrounding structures and requires appropriate medical treatment.
Likewise, suspected spinal infection requires urgent diagnostic evaluation rather than routine treatment for chronic back pain. ACR guidance identifies suspected infection as a red-flag scenario where appropriate imaging evaluation is needed.
Symptoms that may prompt concern can include a combination of:
- Significant new swelling
- Heat or redness
- Fever
- Severe worsening pain
- Recent surgery or injection
- Systemic illness
A painful, hot, swollen joint should be evaluated before assuming it is simply arthritis.
6. Elbow Pain From Repetitive Use: Possibly
Repetitive-use elbow pain often involves tendinopathy, including conditions commonly called:
- Tennis elbow
- Golfer’s elbow
Orthobiologic treatments such as PRP and cell-based approaches have been studied for chronic tendinopathies.
The evidence is not uniform.
A 2025 review of orthobiologics for tendon injuries concluded that PRP, bone-marrow-derived treatments, and other biologic approaches are increasingly used, but evidence supporting routine use remains mixed.
Another contemporary guideline review noted that PRP has shown favorable patient-reported outcomes in some conditions including lateral epicondylitis, while emphasizing substantial study heterogeneity.
That makes chronic repetitive-use pain a reasonable evaluation category, not a guaranteed treatment indication.
7. Heel Pain When You Walk: Possibly
Heel pain can come from several structures.
Common possibilities include:
- Plantar fascia
- Achilles tendon
- Bursae
- Bone
- Nerve irritation
- Other foot and ankle conditions
Orthobiologics have been studied in chronic plantar fasciitis and tendinopathy, particularly PRP.
Current evidence reviews describe possible benefits in selected chronic tendon conditions while also highlighting inconsistent protocols and variable evidence quality.
Before treating heel pain, the provider should determine what structure is actually causing it.
8. Nagging Tendon Pain: Possibly
Long-standing tendon pain is different from an acutely ruptured tendon.
Chronic tendinopathy may involve:
- Achilles tendon
- Patellar tendon
- Rotator cuff
- Common extensor tendon at the elbow
- Gluteal tendons
- Other sites
Researchers continue to study PRP, bone marrow aspirate concentrate, MSCs, and other biologic approaches for tendon disease.
However, the literature remains mixed, and high-quality evidence supporting routine cell-based treatment is still limited.
This makes chronic tendon pain one of those situations where the answer is:
Potentially, depending on the diagnosis, severity, duration, and previous treatments.
9. Torn Cartilage or Meniscus in the Knee: It Depends
“Torn cartilage” can mean several different things.
A patient may have:
- An acute meniscal tear
- A chronic degenerative meniscal tear
- Articular cartilage damage
- An osteochondral injury
- Multiple problems at once
The tear pattern matters enormously.
AAOS guidance for acute meniscal injuries notes that some nondisplaced tears may be treated nonoperatively, while displaced tears restricting motion and certain repairable tears may benefit from early surgery. PRP and bone marrow venting currently have only limited-strength support as biologic augmentation alongside surgical repair in selected acute meniscal cases.
So:
Meniscus tear does not automatically equal regenerative injection.
It also does not automatically equal surgery.
Imaging, symptoms, age of the tear, stability, and mechanical symptoms all matter.
10. Fully Torn Ligament: Yes, With a Big Caveat
This is probably the line in Dr. Dame’s video that most needs explanation.
There is a major difference between:
supporting biology around an injured ligament
and
restoring mechanical stability after a complete rupture.
A completely torn ACL in an active patient, for example, may leave the knee mechanically unstable.
Current AAOS guidance strongly favors reconstruction over repair for common midsubstance ACL tears when surgical management is appropriate. Earlier reconstruction may also be recommended in acute isolated ACL tears because delaying surgery can increase the risk of additional meniscal and cartilage injury.
Cell-based treatments and PRP are being investigated in ligament medicine, including as adjuncts to surgical procedures, but evidence remains incomplete and protocols are not standardized.
So the caveat is:
Regenerative treatment should not be assumed to mechanically reconnect every completely torn ligament.
Sometimes surgery and biologics may be separate or complementary conversations.
11. Completely Worn-Down Joints: Expectations Matter
What patients often call a:
“bone-on-bone joint”
usually refers to advanced osteoarthritis with substantial cartilage loss.
Cell-based treatments have been studied extensively in knee osteoarthritis, and recent randomized-trial meta-analyses report potential improvements in pain and function.
But symptomatic improvement is not the same thing as rebuilding a severely destroyed joint.
A regenerative injection cannot be assumed to:
- Recreate normal cartilage
- Correct severe deformity
- Restore major mechanical instability
- Replace missing joint structure
- Guarantee avoidance of joint replacement
The more structurally advanced the problem, the more important it becomes to discuss realistic goals.
For some patients, the goal may be symptom improvement or maintaining function.
For others, orthopedic surgical evaluation may make more sense.
12. Joint Pain From Aging: Maybe, but Don’t Blame Everything on Age
Joint pain becomes more common with age.
But age itself is not a diagnosis.
An older adult with knee pain might have:
- Osteoarthritis
- Meniscus degeneration
- Tendinopathy
- Hip pathology referring pain to the knee
- Inflammatory arthritis
- Neurological disease
- Another musculoskeletal condition
Being older does not automatically make someone a better or worse candidate.
What matters more is:
- Diagnosis
- Structural damage
- Overall health
- Functional goals
- Previous treatment
- Medical risk
- Expectations
13. What Makes Someone a Better Candidate?
There is no universal checklist, but someone may be more reasonable to evaluate when:
The Diagnosis Is Clear
You know which joint or tissue is actually causing the symptoms.
The Problem Is Chronic or Degenerative
Many regenerative approaches are studied primarily in chronic rather than undiagnosed emergency injuries.
Conservative Care Has Not Been Enough
Depending on the condition, patients may previously have tried:
- Physical therapy
- Activity modification
- Strengthening
- Weight management
- Medications
- Other injections
The Joint Is Mechanically Stable Enough
If the main problem is severe instability or a structure that needs surgical reconstruction, biologic treatment alone may not address the mechanical issue.
There Is No Active Infection
Elective injections should not proceed into or around an active infectious process.
Expectations Are Realistic
A patient should understand that the goal may be improvement in pain or function.
It should not be presented as guaranteed tissue regeneration or guaranteed avoidance of surgery.
14. When Regenerative Joint Treatment May Not Be the Best Next Step
Sometimes the most valuable thing a regenerative provider can say is:
“I don’t think this is the right treatment for you right now.”
Reasons could include:
- Active infection
- Undiagnosed acute trauma
- Fracture
- Dislocation
- Severe instability
- A displaced meniscal tear
- A complete structural injury that needs surgical evaluation
- Significant neurological symptoms
- Suspected spinal infection
- Advanced disease where another intervention offers a more predictable result
- Unrealistic expectations
The FDA also continues to state that regenerative medicine products have not been approved for orthopedic conditions including osteoarthritis, tendonitis, disc disease, tennis elbow, back pain, hip pain, knee pain, neck pain, or shoulder pain.
That FDA status should be part of an informed candidacy discussion.
15. What Happens During a Regenerative Joint Evaluation?
At The Re/ Clinic, the purpose of the consultation should be to determine whether regenerative treatment is appropriate rather than starting with the assumption that treatment will be performed.
The evaluation may include:
Your Diagnosis
What condition has actually been diagnosed?
Your Imaging
Depending on the problem, the provider may review:
- X-rays
- MRI
- CT
- Previous imaging reports
Your Symptoms
Important questions include:
- Where does it hurt?
- How long has it hurt?
- Was there an injury?
- Does the joint lock?
- Does it give out?
- Is there numbness or weakness?
- Is there significant swelling?
- What activities are limited?
Previous Treatment
What have you already tried?
Your Goals
Are you trying to:
- Walk with less discomfort?
- Return to exercise?
- Play a sport?
- Avoid or delay surgery?
- Improve day-to-day function?
Candidacy and Alternatives
A good consultation should discuss more than one possible treatment path.
That can include:
- Physical therapy
- Strengthening
- Activity modification
- Conventional medical treatment
- Orthopedic referral
- Surgery
- PRP
- Other regenerative approaches
- No procedure at all
The Re/ Clinic currently describes regenerative medicine and umbilical cord-derived therapies as part of its musculoskeletal treatment program in Sandy, Utah.
Frequently Asked Questions
Who is a good candidate for stem cell joint therapy?
There is no single profile.
Patients who commonly explore regenerative treatment include those with chronic osteoarthritis, persistent joint pain, tendinopathy, and certain cartilage, meniscal, tendon, or ligament problems.
Candidacy still depends on diagnosis, severity, stability, imaging, overall health, previous treatments, and patient goals.
Can stem cells treat knee arthritis?
Cell-based therapies are actively studied for knee osteoarthritis.
Recent meta-analyses of randomized trials have found potential improvements in pain and function, but studies vary significantly in product, source, dose, and methodology.
These products are not FDA-approved for knee osteoarthritis.
Can regenerative treatment help bone-on-bone arthritis?
Patients with advanced osteoarthritis may still discuss nonsurgical options, but a severely damaged joint is fundamentally different from mild or moderate degeneration.
Regenerative treatment should not be presented as guaranteed to regrow a completely lost joint surface.
For advanced disease, orthopedic joint-replacement evaluation may also be appropriate.
Can you get stem cells for a torn ACL?
Biologic therapies are being investigated in ligament injuries, but a completely torn ACL can create significant mechanical instability.
When surgical management is indicated, AAOS currently favors ACL reconstruction over repair for common midsubstance ACL tears.
A regenerative injection should not automatically be viewed as a replacement for reconstruction.
Can regenerative therapy help a torn meniscus?
It depends on the tear.
An acute displaced tear causing restricted motion may need early orthopedic surgery, while other tears may be managed differently.
AAOS notes limited evidence for biologic augmentation such as PRP or bone marrow venting during surgical meniscal repair.
Can stem cells help tendon pain?
Orthobiologics are being researched for chronic tendon conditions.
Evidence varies by tendon and product, and current reviews characterize the evidence as mixed rather than definitive.
Can I get regenerative treatment right after an injury?
A new injury should generally be diagnosed first.
Some acute injuries require imaging, immobilization, orthopedic treatment, or surgery.
Regenerative treatment should not delay appropriate management of fractures, dislocations, unstable tears, or other significant injuries.
Can I get a joint injection if I have an infection?
An active infection needs to be addressed before an elective regenerative procedure.
A hot, swollen, acutely painful joint should be medically evaluated to determine the cause.
Can regenerative treatment help chronic back pain?
Possibly in selected patients, but chronic back pain has many causes.
Determining the pain generator is essential before discussing an intervention.
The FDA has not approved regenerative medicine products for back pain or disc disease.
Does inflammation mean I am not a candidate?
Not necessarily.
Osteoarthritis and many chronic musculoskeletal conditions involve inflammatory signaling.
What is more concerning is new or unexplained acute inflammation, particularly a hot, swollen joint where infection, trauma, gout, or another acute condition has not been ruled out.
Am I too old for regenerative joint treatment?
Age alone does not determine candidacy.
Structural damage, overall health, diagnosis, goals, joint stability, and other medical factors are more useful considerations.
How do I know if regenerative treatment is right for me?
The best way to determine candidacy is to review your medical history, symptoms, diagnosis, imaging, previous treatment, and goals with a qualified medical provider.
The Best Candidate Is an Informed Candidate
The question should never simply be:
“Do stem cells work for joint pain?”
A better set of questions is:
What is causing my pain?
How severe is the damage?
Is the joint mechanically stable?
What other treatments should I consider?
What does the current research actually support?
And what outcome is realistic for me?
At The Re/ Clinic in Sandy, Utah, regenerative consultations are designed to help determine whether a patient may be appropriate for treatment and what alternatives should also be considered.
If you have chronic knee, shoulder, back, elbow, tendon, or other musculoskeletal pain, the first step is understanding the diagnosis.
Schedule a regenerative medicine consultation with The Re/ Clinic to find out whether you may be a candidate.
Call: 385-240-1000
Location: 9035 S 700 E, Sandy, UT 84070
References
- U.S. Food and Drug Administration. Important Patient and Consumer Information About Regenerative Medicine Therapies. FDA states that regenerative medicine products are not approved for orthopedic conditions including osteoarthritis, tendonitis, disc disease, back pain, knee pain, hip pain, neck pain, and shoulder pain.
- American Academy of Orthopaedic Surgeons. Clinical Practice Guideline for Management of Acute Isolated Meniscal Pathology. 2024. Includes guidance regarding imaging, displaced tears, surgical repair, physical therapy, and limited evidence for biologic augmentation.
- American Academy of Orthopaedic Surgeons. Clinical Practice Guideline for Management of Anterior Cruciate Ligament Injuries. Updated 2022. Current recommendations include reconstruction considerations and timing of surgical intervention for acute ACL injuries.
- American Academy of Orthopaedic Surgeons. Clinical Practice Guideline for Management of Rotator Cuff Injuries. Updated 2025.
- Cao M, et al. Efficacy and safety of mesenchymal stem cells in knee osteoarthritis: a systematic review and meta-analysis of randomized controlled trials. Stem Cell Research & Therapy. 2025.
- Systematic review and meta-analysis of randomized controlled trials evaluating MSC therapy for osteoarthritis. 2026. Current evidence reports potential improvement in pain and function while highlighting variability across clinical trials.
- Eliasberg CD, Rodeo SA. Orthobiologics for Tendon Injuries. Clinics in Sports Medicine. 2025. Current review describing mixed evidence for PRP, BMAC, and other orthobiologics in tendon disorders.
- Evidence-Based Guidelines on Orthobiologics. 2025. Review of PRP and cell/tissue-based orthobiologics, their clinical applications, limitations, and heterogeneity.
- American College of Radiology. ACR Appropriateness Criteria: Low Back Pain. Current diagnostic guidance distinguishing uncomplicated chronic low-back pain from red-flag scenarios including infection and cauda equina syndrome.
- Utah Code § 58-1-512. Stem Cell Disclosure. Effective May 6, 2026. Requires the statutory disclosure for applicable non-FDA-approved stem cell therapy and applicable advertising.
Utah Stem Cell Therapy Notice
THIS NOTICE MUST BE PROVIDED TO YOU UNDER UTAH LAW.
This health care practitioner performs one or more stem cell therapies that have not yet been approved by the United States Food and Drug Administration.
You are encouraged to consult with your primary care provider before undergoing a stem cell therapy.